The second location is where a dental practice stops being a place and becomes an organisation. Most of what made the first clinic work was proximity: the owner saw what happened, staff spoke to each other, and problems were noticed because someone was standing there. None of that survives a second address.
This covers what actually changes when a practice opens a second site, which decisions have to be made deliberately because they were previously implicit, and where clinic software helps and where it does not.
What stops working automatically
Single site practices run on shared context. Everyone knows which dentist is in, which patients are difficult, what the convention is for booking a long appointment. None of this is written down because it never needed to be.
At two sites the same knowledge has to travel, and it does not travel by itself. Four things break first.
The owner stops seeing things. Whichever site the owner is not at is now run on trust and reporting. Problems that used to be noticed on the way past the desk now surface weeks later, usually in a number.
Conventions diverge. Two reception teams solving the same problem independently will solve it two different ways within a month. Neither is wrong. They are simply different, and patients who attend both sites notice.
Patients become ambiguous. Someone registered at one site attends the other. Are they one patient or two? If the systems are separate, they are two, and their history is split from that moment.
Staff cover across sites. A receptionist covering a shift at the other location needs access, needs to know that site's conventions, and needs the same patient records. Each of those is trivial at one site and a decision at two.
One dataset or two
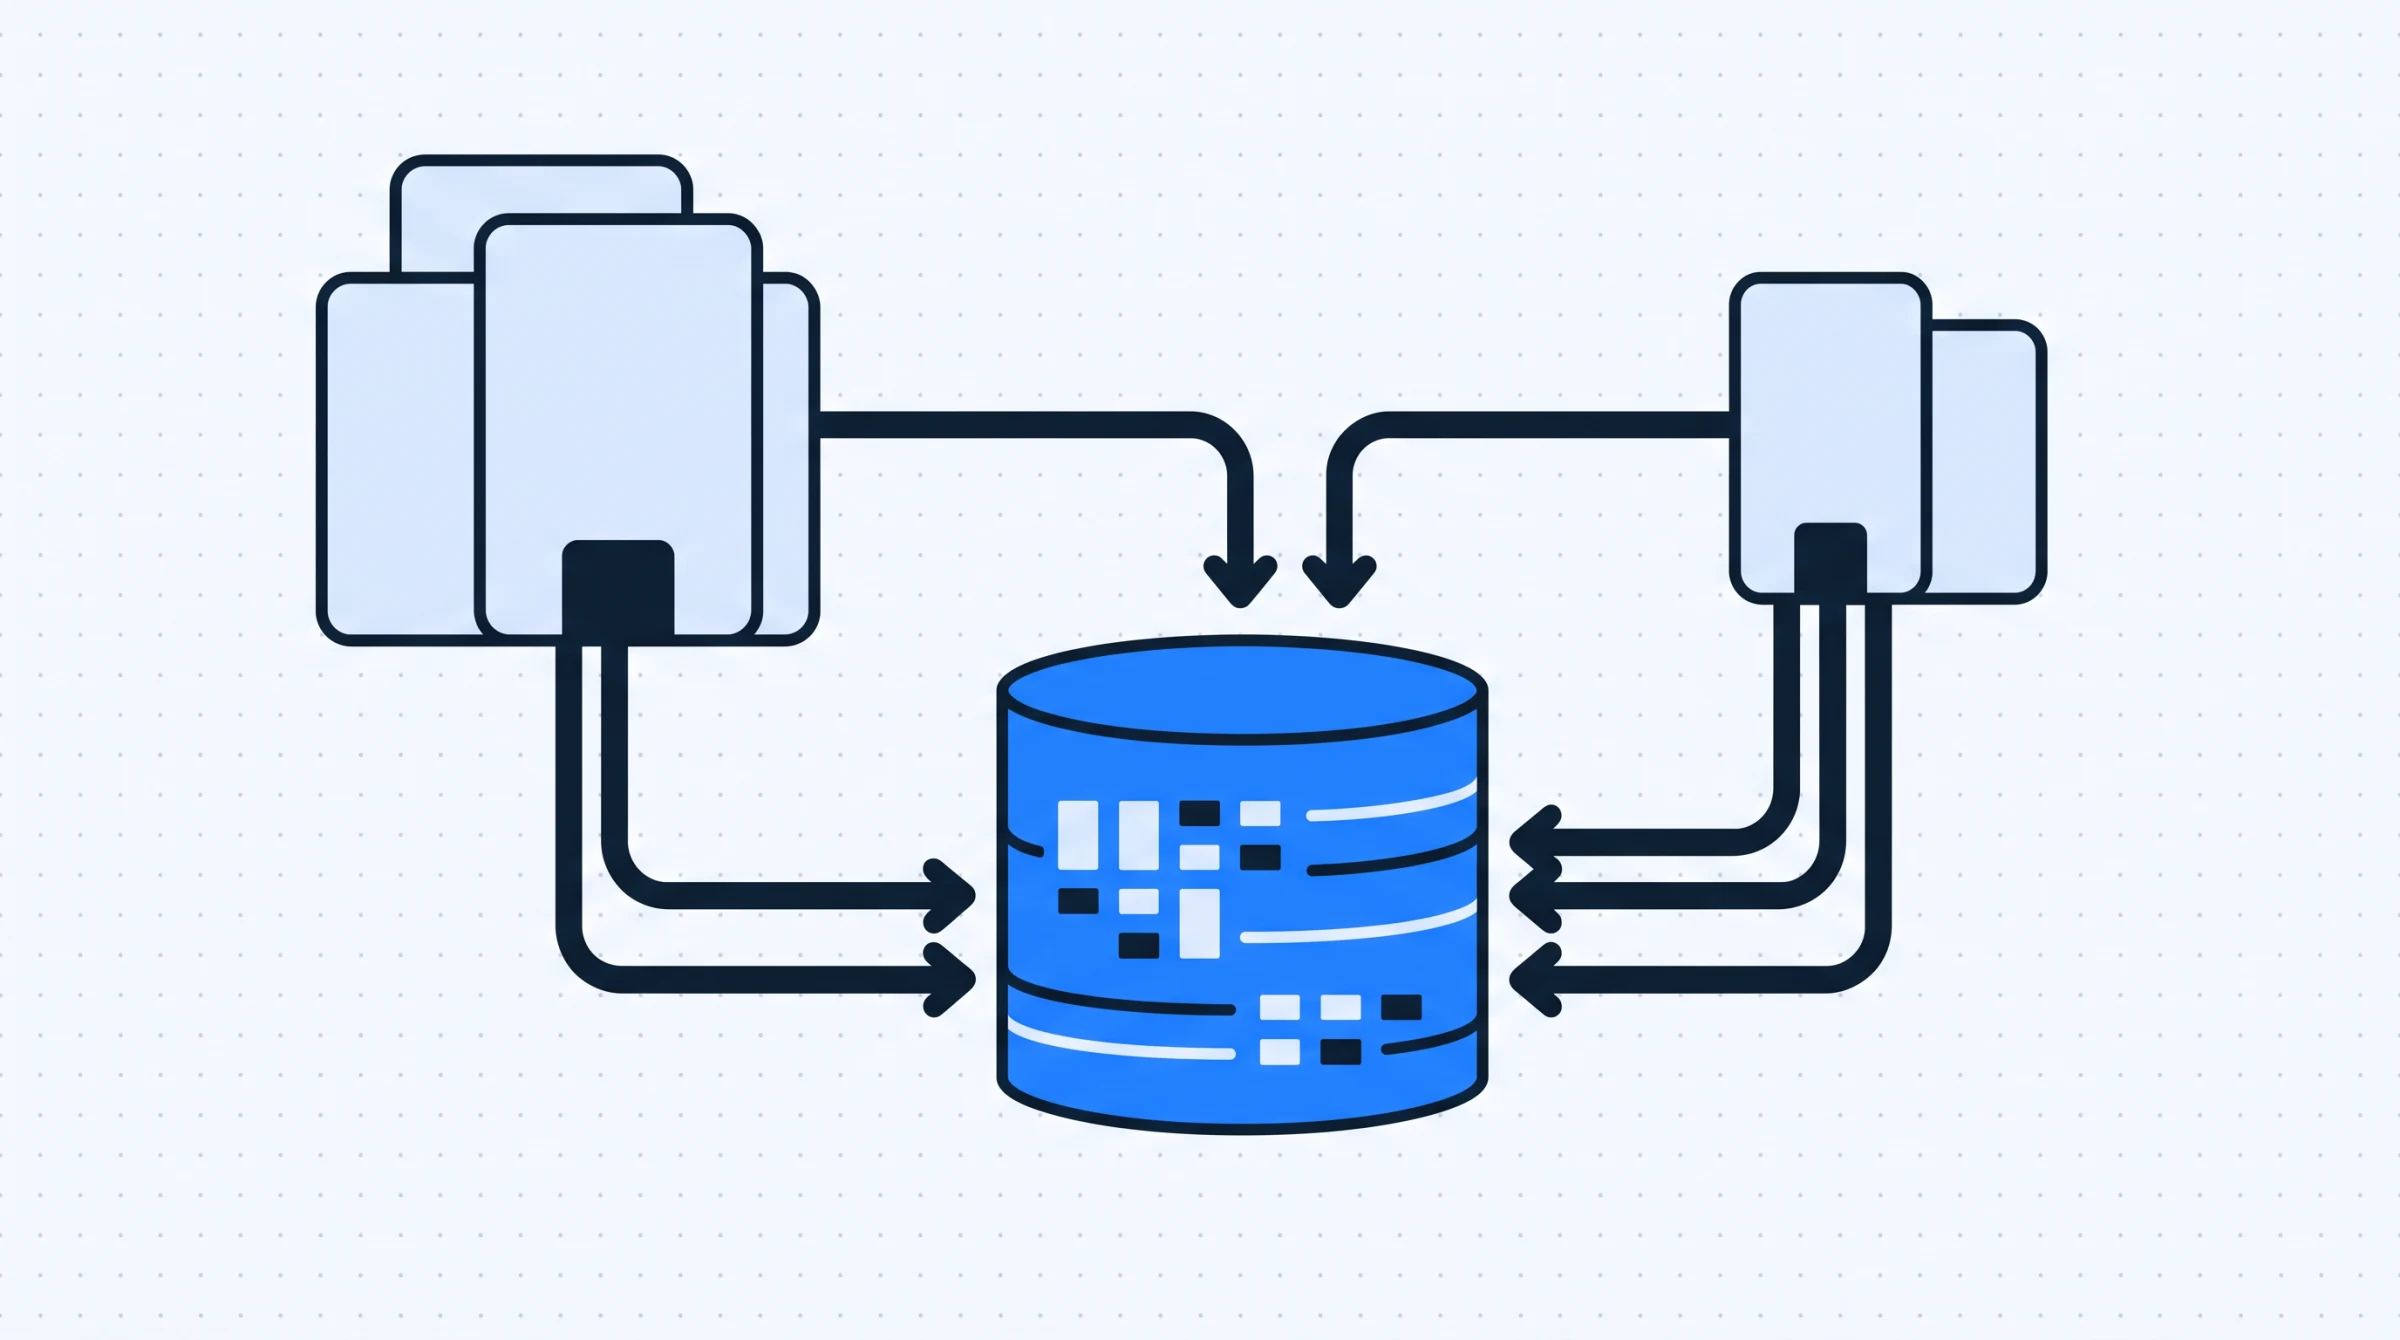
This is the decision that constrains everything else, and it is worth making explicitly rather than by default.
| Shared records | Separate per site | |
|---|---|---|
| Patient attends both sites | One history, visible at both | Two records, each partial |
| Staff cover the other site | Same login, same view | Second account, different data |
| Owner wants combined figures | Already combined | Manual consolidation |
| Sites have different treatments | Needs per site configuration | Naturally separate |
| One site is sold or closed | Requires disentangling | Clean separation |
For most practices the shared arrangement is correct, because the top three rows describe daily events and the bottom two describe rare ones. The exception is where the sites are genuinely separate businesses with different ownership, in which case separation reflects reality rather than fighting it.
The shared model has one requirement that is easy to miss: everything must be attributable to a site. Every appointment, payment and expense needs to know where it happened, or the combined view is the only view and per site questions become unanswerable. That attribution is much easier to set up at the start than to add afterwards.
What has to be decided rather than assumed
A second site turns several implicit arrangements into choices. Making them consciously saves an argument later.
- Can a patient be seen at either site without ceremony? Most practices say yes and then discover their records assume otherwise.
- Do prices match across sites? Different rents and local markets argue for difference; patients who visit both argue against it.
- Who books for the other site? If reception at site A can fill site B's calendar, utilisation improves and conflicts become possible.
- Where does a patient's balance sit? If they owe money from one site and attend the other, someone has to be able to see it and take payment.
- Which site does a referral belong to? The one that received it, or the one that treated it, which may differ.
None of these has a single right answer, and the cost of getting one wrong is usually modest. The cost of never deciding is higher, because the two sites then answer differently and the inconsistency becomes visible to patients before it becomes visible to the owner.
Question four causes the most friction in practice, because it sits between clinical and financial systems and is the kind of thing nobody thinks about until a patient is standing at a desk that cannot see what they owe.
Reporting that answers the right question
Multi site reporting has a trap: the combined number hides the thing you need to know.
A practice whose overall collections are flat may have one site growing and another declining, which is a completely different situation from two stable sites. Any figure worth looking at monthly should be available per site and combined, and the per site view should be the default.
Three comparisons repay attention once both sites have a few months of history. Cost per working day at each, which differs more than owners expect because rent and staffing rarely scale together. New patient numbers by site, which reveals whether the second location is finding its own market or splitting the first one. And chair utilisation, which is the number that tells you whether the second site was a capacity decision that worked.
Be careful comparing sites directly on revenue. A newer location with a smaller list will look worse for a year or more regardless of how well it is run, and judging it against the established site produces decisions based on age rather than performance.
The patient's experience of two addresses
Practices plan the operational side of a second location carefully and the patient side barely at all, which is where most of the avoidable irritation comes from.
Patients do not experience your sites as one organisation unless you make them. They experience a clinic they know and another place with the same name. That is fine until something reveals the seam: being asked for details they gave at the other site, a receptionist who cannot see their balance, or a treatment plan the second site knows nothing about.
Each of those is a records problem wearing a service costume. A patient asked to re register at the second location has been told, accurately, that the practice keeps two sets of books. Nothing said afterwards about being one practice will carry much weight.
The decisions that matter to patients are small and specific. Whether they can book at either site by calling either number. Whether their recall reminder tells them which location. Whether a balance can be settled anywhere. Whether a dentist at the second site can see what the first one planned. Getting these right is largely a function of keeping one record per patient rather than of any policy.
Be clear in signage and communications about what differs, particularly opening hours and which treatments are available where. A patient who travels to the wrong site for a service it does not offer will remember that longer than any amount of smooth booking.
Staffing and access across sites
Cover is the most common operational reason to want shared systems, and it is where access arrangements usually fall apart.
The workable rule is that a person has one account that works everywhere they are entitled to work, rather than a separate identity per site. Two accounts for one person means two passwords, two sets of permissions to maintain, and an account that is forgotten when they leave.
What varies by site is not who someone is but what they can do there. A practice manager responsible for one location may need financial visibility there and not at the other. Systems that support defined roles including custom ones handle this by attaching scope to the role rather than multiplying accounts.
Agree what a covering member of staff is expected to know. Handing someone the other site's login without telling them that appointments there are booked in different default lengths produces an afternoon of quiet errors. A short written note per site, covering the half dozen conventions that differ, is worth more than any amount of system configuration.
Opening the second site without importing the chaos
The practical sequence matters. Clinics that run into trouble usually did things in the wrong order rather than doing the wrong things.
Settle the configuration questions before the second site opens, not during its first week. Treatment names, appointment types, default durations and price lists should be agreed while there is time to think, because whatever is set up in the opening fortnight becomes permanent by accident.
Decide who owns cross site consistency, and make it one person. Conventions diverge by default; keeping them aligned is a job someone has to hold rather than a shared intention. That person should visit both sites regularly, which is the only reliable way to notice drift.
Expect the first quarter to be unrepresentative. A new site has a patient list being built, staff learning each other, and an owner splitting attention. Judging the decision on three months of figures is judging the opening rather than the location.
If you want to see how one patient record, one calendar and per site figures fit together before committing to a second address, the feature overview shows the structure, and you can book a demo to work through the five questions above against your own plans.